
Learning differences
Global Developmental Delay: What It Means, the Signs, and What Happens Next
A provisional diagnosis by design — what it means, and why the reassessment is the part that gets missed.
- Editorially Reviewed
- Evidence Based
- Patient Focused
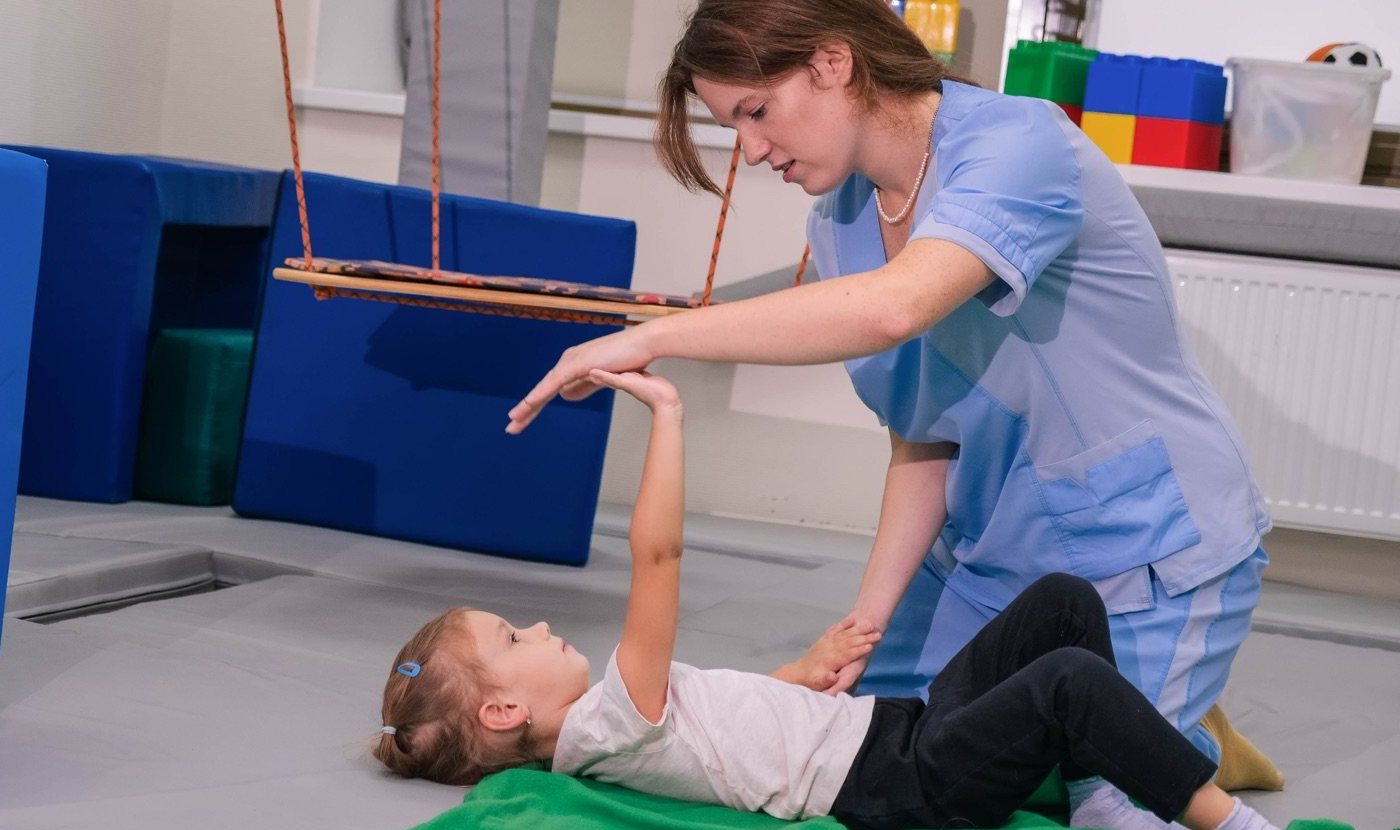
Global developmental delay (GDD) is a DSM-5 diagnosis used for children under five who show significant delays across multiple developmental domains — motor, language, cognitive, social, or daily living skills — where the severity of impairment cannot yet be reliably assessed because the child is too young for standardized testing. It is, by design, a temporary diagnosis. As a child grows and assessment becomes more reliable, the diagnosis is reviewed: some children go on to meet criteria for intellectual disability, some receive a different diagnosis, and some catch up. It requires reassessment after a period of time, and that follow-up is the part most often missed.
Global developmental delay (GDD) is a DSM-5-TR diagnosis for children under five with significant delays across two or more developmental domains, used when the child is too young for standardized testing to establish what is underlying them. It is temporary by design and requires reassessment as the child grows.1 It affects roughly 1–3% of children.3,5 It describes a picture; it does not explain it, and it does not predict what a child will be able to do.
Key Takeaways
- GDD means delays in two or more domains in a child under five — “global” refers to breadth, not severity.1,2
- It affects an estimated 1–3% of children, making it one of the more common developmental diagnoses.3,5
- It is a placeholder, not a verdict. The DSM-5-TR specifies reassessment after a period of time, and in practice that follow-up is frequently missed.1
- Three outcomes are possible — a more specific diagnosis, intellectual disability, or catching up — and none is reliably predictable in a very young child.
- The diagnosis describes; it does not explain. Investigation matters, because some causes are treatable and others change medical monitoring.2
- Chromosomal microarray is the first-tier genetic test, with a diagnostic yield of roughly 15–20% against about 3% for karyotyping.2,4
- Support does not wait for diagnostic clarity. In the US you can refer your own child to early intervention, with no doctor’s referral and no cost.8
- Loss of previously acquired skills is a different question and needs prompt medical evaluation.
What does global developmental delay mean?
It means significant delays across more than one area of development, in a child too young for the assessments that would establish what is underlying them.
It does not mean a prediction. Global developmental delay describes a picture at a point in time. It is not a statement about what a child will be able to do.
“Global” refers to multiple domains, not to severity. A delay in one area alone is not global developmental delay. A child with a significant speech delay and typical motor, cognitive, social and self-care development has a speech delay, not GDD.
The diagnosis is defined by delays involving significant impairment in two or more domains: gross or fine motor skills, speech and language, cognitive functioning, social and personal development, and activities of daily living.1,2,3
How common is global developmental delay?
Global developmental delay and intellectual disability together affect approximately 1–3% of children.3,5
That figure is worth holding onto for two reasons. It means this is not rare, and you are not alone in a way that matters practically — services exist, pathways exist, and other families in your area are navigating the same thing. And it means clinicians see this regularly, so a request for proper investigation and a scheduled reassessment is a routine ask, not an unusual demand.
What are the five developmental domains?
| Domain | What it covers | Who typically assesses |
|---|---|---|
| Gross and fine motor | Sitting, walking, climbing; grasping, drawing, using utensils | Physical therapist, occupational therapist |
| Speech and language | Understanding and using language, including non-speaking communication | Speech-language pathologist |
| Cognitive | Problem-solving, memory, learning, play complexity | Psychologist, developmental pediatrician |
| Social and personal | Interaction, shared attention, emotional response | Developmental pediatrician, psychologist |
| Daily living (adaptive) | Feeding, dressing, toileting, self-care | Occupational therapist |
Delays in two or more of these constitute the “global” in global developmental delay. Understanding which domains are affected matters more practically than the label itself, because it determines which therapies your child needs.
What are the signs of global developmental delay?
There is no single sign. Global developmental delay is diagnosed when a child is significantly behind in two or more domains, so the signs are the ordinary milestones, missed together.
The table below lists what the CDC's revised checklists say most children can do at each health supervision visit. "Most" is a defined threshold: the working group that produced them used milestones that at least 75% of children would be expected to have reached by that visit, chosen deliberately so that a missed milestone prompts a conversation rather than a wait-and-see.7
| By this age, most children | Movement | Language | Cognitive and play | Social |
|---|---|---|---|---|
| 12 months | Pull up to stand; walk holding on to furniture; pick things up between thumb and finger | Wave bye-bye; call a parent “mama” or “dada”; pause when you say “no” | Put something into a container; look for a toy they saw you hide | Play games with you, such as pat-a-cake |
| 18 months | Walk without holding on; scribble; climb on and off a chair unaided | Try to say three or more words besides mama and dada; follow a one-step direction without gestures | Copy you doing chores; play with a toy in a simple way, such as pushing a car | Point to show you something; help you dress them by pushing an arm through a sleeve |
| 24 months | Run; walk up a few stairs with or without help; eat with a spoon; kick a ball | Say at least two words together; point to things in a book when asked; point to two body parts | Hold something in one hand while using the other; play with more than one toy at a time | Notice when someone else is hurt or upset; look at your face to see how to react |
| 30 months | Jump off the ground with both feet; take some clothes off; twist a doorknob or a lid | Say about 50 words; put two or more words together with an action word; name things in a book | Pretend, such as feeding a block to a doll; follow a two-step instruction; know at least one color | Play next to other children and sometimes with them; follow a simple routine when told |
| 36 months | String large beads; put on some clothes unaided; use a fork | Talk well enough for most people to understand; hold a conversation with two back-and-forth turns; ask who, what, where or why | Draw a circle when shown how; avoid touching something hot when warned | Notice other children and join them to play; settle within about ten minutes of being left |
Missing one of these is a reason to ask, not a diagnosis. Missing several, across two or more of these columns, is the picture the diagnosis describes and the point at which an evaluation is warranted.7
Two things change the urgency. A child who has lost a skill they had — words, movement, engagement — needs prompt medical assessment rather than a milestone chart; that is regression, and it is covered below. And a child with significant delays alongside seizures, a marked change in muscle tone, or unusual head growth needs neurology sooner rather than later.
What the signs do not tell you is why. Two children with the same missed milestones may have entirely different causes, or none that can be identified. That is what the investigations are for, and it is the next section.
Why is global developmental delay a temporary diagnosis?
This is the most important thing on the page.
The diagnosis exists because standardized cognitive and adaptive testing is not reliable in very young children. It is a placeholder that says: significant delays are present, and we cannot yet characterize them properly.
The DSM-5-TR specifies that the diagnosis requires reassessment after a period of time.1
In practice, that follow-up frequently does not happen. Families are given the diagnosis, connected to services, and the review never gets scheduled — leaving a placeholder label in place for years, sometimes into school age, where it stops describing the child accurately and starts limiting what is asked of the system.
Four questions to ask at the appointment
A diagnosis of global developmental delay should come with a plan to revisit it. These four questions get that plan on the record, and they are best asked at the appointment where the diagnosis is given rather than afterwards.
Take these with you
- When will my child be reassessed? A date, or at least an interval.
- Who will arrange it? Whether it falls to the clinic, the school, or you.
- What will that assessment involve? Which professionals, and what they will be looking at.
- What would change the diagnosis? What findings would move it toward something more specific.
Write the answers down before you leave. If nobody has scheduled a review, that is worth chasing — and chasing it is a reasonable thing for a parent to do, not a difficult one.
What happens to children with global developmental delay as they grow?
Three broad outcomes, and no reliable way to predict which in a very young child.
A more specific diagnosis emerges. As development unfolds and assessment becomes possible, the picture may resolve into autism, a specific learning disorder, a genetic condition, or another identified cause.
Intellectual disability is diagnosed. Where difficulties across intellectual and adaptive functioning persist and can be reliably assessed, this becomes the diagnosis. See intellectual disability.
The child catches up. Some children with early delays across multiple domains go on to develop within typical ranges.
Anyone who tells you confidently which of these applies to a two-year-old is going beyond what can be known. That uncertainty is uncomfortable, and it is honest.
Global developmental delay vs. intellectual disability vs. autism
These get confused constantly, and the distinctions are practical rather than academic.
| Global developmental delay | Intellectual disability | Autism | |
|---|---|---|---|
| Age | Under 5 | Any age, once reliably assessable | Any age |
| What it describes | Delays across two or more domains, severity not yet assessable | Deficits in intellectual and adaptive functioning, assessed and characterized | Social communication differences plus restricted or repetitive patterns, including sensory reactivity |
| Permanence | Provisional — requires reassessment | A standing diagnosis | A standing diagnosis |
| Can they co-occur? | GDD may resolve into either | Frequently co-occurs with autism | Frequently co-occurs with intellectual disability |
The most common misunderstanding is that GDD is a milder version of intellectual disability. It is not a severity level. It is a statement that the assessment cannot yet be done — which is a different kind of claim entirely.
What tests should be done for global developmental delay?
Global developmental delay describes a picture. It does not explain it — and the search for an explanation matters, because some causes are treatable and others change medical monitoring.2
First, always
Hearing and vision. Always, and first. Both affect development across every domain, both are common, and both are treatable. A child who cannot hear well will show language, social and cognitive delays that resolve with treatment.
Genetic testing
Chromosomal microarray is the recommended first-tier genetic test for children with unexplained developmental delay or intellectual disability. It offers a diagnostic yield of 15–20%, compared with approximately 3% for a G-banded karyotype, primarily because of its higher sensitivity for submicroscopic deletions and duplications.4 It has been described as the single most efficient diagnostic test for GDD after history and examination.2
Karyotyping is now reserved for children with an obvious chromosomal syndrome such as Down syndrome, a family history of chromosomal rearrangement, or a history of multiple miscarriages.4
Where the field is moving: a 2025 meta-analysis of 102 studies covering 55,752 children compared exome sequencing with microarray in children with GDD or intellectual disability, and found diagnostic yields of 33–41% for whole exome sequencing against 16–21% for microarray, concluding that incorporating exome sequencing as a first-line investigation may be warranted.3 Worth asking your genetics team about, particularly if microarray comes back negative.
Other investigations, as indicated
- Metabolic screening. Yield is modest — between 0.2% and 4.6% depending on clinical signs and the range of tests used — but some metabolic conditions are treatable when identified early, which is why it stays on the list. The free tool at treatable-id.org helps clinicians target testing for treatable inherited metabolic conditions.2
- Neurological assessment, with MRI where indicated. Diagnostic yield is higher when GDD occurs alongside clinical signs such as abnormal head circumference — microcephaly, non-familial macrocephaly, or rapid change in head growth — focal neurological signs, or epilepsy.2
- Thyroid function.
- Lead exposure, depending on setting and history.
- A review of pregnancy, birth and medical history.
If your child has a global developmental delay diagnosis and no investigation has been done, ask about it. Same principle as hypotonia — the diagnosis names what is observed, not why.
On a negative result: a normal microarray does not mean nothing is there. It means that particular test did not find it. Many children never receive a causal explanation, and re-analysis of genetic data some years later sometimes yields an answer that was not available at the time.
When does developmental delay need urgent attention?
If your child has lost skills they previously had, that is investigated differently from delay and warrants prompt medical evaluation.
Delay means a skill is arriving late. Regression means a skill arrived and then went. These are different clinical questions with different urgency, and the distinction is frequently lost when a parent describes it in passing.
Say it explicitly when seeking help: “He was using twenty words at eighteen months and now uses four.” That sentence changes the pathway. See developmental regression.
Also raise promptly: seizures, a marked change in muscle tone, loss of head control, or any sudden change in a previously stable picture.
How do I start therapy before the diagnosis is settled?
The single most useful thing to know: you do not need a resolved diagnosis to start.
Early intervention, birth to three
In the US, every state runs an early intervention program for children under three under IDEA Part C, free of charge. You can refer your own child — no doctor’s referral, no cost, regardless of income or insurance. Search “[your state] early intervention.”
Federal regulation requires the evaluation, the assessment, and the meeting to write the plan to be completed within 45 days of referral.8
From age three
Services move to the school district. Request an evaluation in writing to start the timeline. A written request is what creates the legal clock; a conversation at pickup does not.
Which therapies
- Physical therapy — motor development, strength, mobility, postural control
- Occupational therapy — daily living, fine motor, feeding, and sensory processing, which frequently accompanies developmental delay
- Speech-language pathology — communication, including AAC, and feeding
On AAC specifically: if your child is not speaking, the common worry is that introducing communication supports will delay speech. In the best-evidence analysis of the research, no case showed a decrease in speech production following AAC intervention; most showed modest gains. The review covered 27 cases and notes that most of the wider literature lacked experimental control, so this is reassuring rather than definitive — but it points one way only.6 See oral motor development for speech and feeding.
Intervention during early childhood targets the period when development is most responsive. Waiting for diagnostic clarity spends that period.
Our cost and insurance guides cover funding, and you can browse providers by state.
What do parents of a newly diagnosed child need to know?
A diagnosis that does not explain anything and cannot predict anything is a hard thing to be handed.
Three things worth holding onto.
The uncertainty is real. It is not information being withheld, and pressing for a clearer answer usually will not produce one, because the assessment tools genuinely do not work reliably at this age.
The uncertainty does not prevent action. Everything useful — therapy, early intervention, medical investigation — proceeds without it.
The label is a key, not a verdict. Its main function right now is unlocking services. It is not a description of who your child is or a forecast of who they will become, and it is explicitly designed to be revisited.1
Practically: keep one folder with every report, note the date of every appointment and who said what, and write down the reassessment plan. You will be the only person holding the whole picture, and that is worth accepting early rather than discovering later. Milestone checklists used in routine surveillance are a useful reference point for what is being tracked and when.7
Frequently Asked Questions
What is global developmental delay (GDD)?
A DSM-5-TR diagnosis for children under five with significant delays across two or more developmental domains — motor, language, cognitive, social, or daily living skills — where severity cannot yet be reliably assessed because the child is too young for standardized testing. It affects roughly 1–3% of children and is a temporary category that requires reassessment.
Does “global” mean severe?
No. It refers to multiple developmental domains being affected, not to how significantly. A child can have mild delays across several domains and meet criteria, while a child with a single severe delay does not.
How common is global developmental delay?
Global developmental delay and intellectual disability together affect approximately 1–3% of children. It is not a rare diagnosis, which means established pathways and services exist for it.
Will my child catch up?
Some children do. Others go on to receive a more specific diagnosis, and some meet criteria for intellectual disability. It is not reliably predictable at a young age, which is precisely why the diagnosis is reviewed over time. Anyone offering a confident prediction for a two-year-old is going beyond what can be known.
Is global developmental delay the same as intellectual disability?
No. GDD is a temporary diagnosis for children under five, used when testing is not yet reliable. Intellectual disability is diagnosed when deficits in intellectual and adaptive functioning can be properly assessed and characterized. Some children with GDD later meet criteria for intellectual disability, some receive a different diagnosis, and some catch up.
What tests should be done for global developmental delay?
Hearing and vision first, always. Then chromosomal microarray, the recommended first-tier genetic test, with a diagnostic yield of 15–20% compared with around 3% for karyotyping. Metabolic screening, neurological assessment with MRI where indicated, and thyroid function follow as clinically indicated. A 2025 meta-analysis found exome sequencing yields 33–41% against 16–21% for microarray, so it is worth asking your genetics team about.
When should my child be reassessed?
The DSM-5-TR specifies that the diagnosis requires reassessment after a period of time. Ask when it is scheduled, who arranges it, what it will involve, and what would change the diagnosis — and write the answers down. This follow-up is frequently missed, and chasing it is a reasonable thing for a parent to do.
Can we start therapy without a clearer diagnosis?
Yes, and you should. In the US, early intervention is free for children under three under IDEA Part C and a parent can refer their own child without a doctor’s referral, regardless of income. Support is based on developmental need, not on a diagnostic label — and early childhood is the period when development is most responsive, so waiting for clarity spends it.
My child has lost skills they used to have. Is that the same thing?
No. Loss of previously acquired skills is investigated differently from delay and warrants prompt medical evaluation. Delay means a skill is arriving late; regression means it arrived and then went. Say so explicitly when seeking help — that sentence changes the pathway.
Does global developmental delay mean my child is autistic?
Not necessarily. Some children diagnosed with GDD later meet criteria for autism, and the two can co-occur, but GDD describes delay across domains rather than the social communication and repetitive-behavior pattern that defines autism. A proper evaluation should consider both.
What causes global developmental delay?
Often no cause is identified, and that is a common outcome rather than a failure of investigation. Where a cause is found, genetic conditions are the most frequent category — chromosomal microarray identifies a cause in roughly 15–20% of cases. Metabolic conditions, neurological differences, prematurity, and prenatal or birth events account for others.
Will my child need special education?
Possibly, and that decision is made on assessed need rather than on the diagnosis itself. From age three, request an evaluation from your school district in writing. Under-threes are covered by early intervention, which transitions to district services at three.
Is global developmental delay a disability?
It is a diagnosis that qualifies a child for services — early intervention under three, a school district evaluation from three — but it is not a permanent disability label. It is provisional by design and is reviewed as the child grows.
Can global developmental delay be treated?
The delays are addressed through therapy — physical, occupational, speech — and the cause, if one is found, may have its own treatment. Some children catch up, some receive a more specific diagnosis later, and some go on to a diagnosis of intellectual disability. Therapy starts before any of that is settled.
Sources
- American Psychiatric Association. Diagnostic and Statistical Manual of Mental Disorders, Fifth Edition, Text Revision (DSM-5-TR). APA Publishing; 2022. — Global developmental delay (315.8 / F88) is reserved for individuals under the age of 5 years when the clinical severity level cannot be reliably assessed during early childhood. It applies to those who fail to meet expected developmental milestones in several areas of intellectual functioning, including individuals unable to undergo systematic assessment because they are too young. This category requires reassessment after a period of time.
- Mithyantha R, Kneen R, McCann E, Gladstone M. Current evidence-based recommendations on investigating children with global developmental delay. Archives of Disease in Childhood. 2017;102(11):1071. PMID 29054862. — Global developmental delay is defined as significant delay in two or more developmental domains of gross/fine motor, speech/language, cognition, social/personal and activities of daily living, affecting children under the age of 5 years. Chromosome microarray has been described as the single most efficient diagnostic test for GDD after history and examination; across 33 studies in nearly 22,000 patients, diagnostic yield was between 15% and 20%, while karyotyping is 3%. The yield of metabolic investigations varied between 0.2% and 4.6% depending on clinical signs and the range of tests undertaken. The diagnostic yield of MRI is higher where GDD is associated with clinical signs such as abnormal head circumference, focal neurological signs or epilepsy. The free web application at treatable-id.org may be useful for tailoring investigations for treatable inherited metabolic conditions.
- Tengsujaritkul M, Louthrenoo O, Likhitweerawong N, Boonchooduang N, Srisurapanont M. Diagnostic and clinical utility of exome sequencing and chromosomal microarray in children with GDD/ID: a meta-analysis. Annals of Medicine. 2025;58(1):2609424. PMID 41472336. — Global developmental delay and intellectual disability affect approximately 1–3% of children. GDD involves significant impairment in two or more domains: gross or fine motor skills, speech and language, cognitive functioning, social and personal development, and activities of daily living. Across 102 studies conducted in 37 countries and comprising 55,752 children, diagnostic yields were 33–41% for whole exome sequencing and 16–21% for chromosomal microarray, with the authors concluding that incorporating exome sequencing as a first-line investigation may be warranted.
- Miller DT, Adam MP, Aradhya S, et al. Consensus statement: chromosomal microarray is a first-tier clinical diagnostic test for individuals with developmental disabilities or congenital anomalies. American Journal of Human Genetics. 2010;86(5):749–764. PMID 20466091. — Chromosomal microarray offers a much higher diagnostic yield (15–20%) for genetic testing of individuals with unexplained developmental delay or intellectual disability, autism spectrum disorder, or multiple congenital anomalies than a G-banded karyotype (approximately 3%, excluding Down syndrome and other recognizable chromosomal syndromes), primarily because of its higher sensitivity for submicroscopic deletions and duplications.
- Shevell M, Ashwal S, Donley D, et al.; Quality Standards Subcommittee of the American Academy of Neurology and Practice Committee of the Child Neurology Society. Practice parameter: evaluation of the child with global developmental delay. Neurology. 2003;60(3):367–380. PMID 12578916. — Global developmental delay is common and affects 1% to 3% of children. This practice parameter has been retired by the American Academy of Neurology and is cited here as the origin of the prevalence figure and of the investigation framework, not as current guidance.
- Millar DC, Light JC, Schlosser RW. The impact of augmentative and alternative communication intervention on the speech production of individuals with developmental disabilities: a research review. Journal of Speech, Language, and Hearing Research. 2006;49(2):248–264. PMID 16671842. — Of 23 studies identified, 6 involving 27 cases had sufficient methodological rigor for the best-evidence analysis. None of the 27 cases demonstrated decreases in speech production as a result of AAC intervention; 11% showed no change and 89% demonstrated gains, mostly modest. The authors note that 17 of the 23 studies did not establish experimental control, limiting the certainty of the evidence.
- Zubler JM, Wiggins LD, Macias MM, et al. Evidence-informed milestones for developmental surveillance tools. Pediatrics. 2022;149(3):e2021052138. PMID 35132439.
- US Department of Education. 34 CFR §303.310 — Post-referral timeline (45 days), Individuals with Disabilities Education Act, Part C. sites.ed.gov. — The evaluation, assessment and initial IFSP meeting must be completed within 45 days of referral.
Medical disclaimer. This page is for general educational purposes and does not constitute medical advice, diagnosis, or treatment. If your child has lost skills they previously had, contact their doctor promptly.